Chronic nasal obstruction is exhausting in a way that’s hard to explain to someone who breathes freely. You wake up with a dry mouth. You prop yourself up on two pillows just to get enough air. The headaches come in the morning, and the fatigue follows you all day. Functional rhinoplasty is the surgical answer to that pattern, built around one goal: restoring the nasal airway to what it was always meant to be. This is not a cosmetic nose job. It’s structural surgery targeting the anatomical failures that block your breathing.
What makes this procedure genuinely different is that it requires a surgeon who understands the nose as an airway first and an aesthetic structure second. ENT specialists like Op. Dr. Ergün Kürün, who brings over 25 years of surgical experience in both nasal function and rhinoplasty aesthetics, approach every case with airway assessment built into the plan from the start. That dual expertise matters, and this article explains exactly why.
What functional rhinoplasty actually corrects
Three anatomical problems account for the vast majority of surgically correctable nasal obstruction: a deviated septum, enlarged turbinates, and nasal valve collapse. They often coexist, and correcting only one while leaving the others intact frequently produces disappointing results. Understanding each problem separately is the clearest way to understand what this surgery does.
Deviated septum and why straightening it isn’t always enough
The nasal septum is the wall of cartilage and bone that divides your two nasal passages. When it deviates significantly to one side, it narrows that passage and can trigger compensatory enlargement of the turbinate on the opposite side, a feedback effect that compounds the obstruction. Septoplasty, the procedure that straightens this wall, addresses the divider itself but not the structural framework surrounding it. Think of it this way: septoplasty fixes the bent interior wall, but functional rhinoplasty reinforces the doorframe so it doesn’t collapse regardless of what the wall does. For patients whose obstruction involves both problems, septoplasty alone produces limited breathing improvement.
Turbinate hypertrophy: when nasal tissue grows too large
The inferior turbinates are shelf-like structures inside the nose that warm, humidify, and filter incoming air. When they become chronically enlarged, they narrow the airway significantly. Chronic enlargement typically stems from allergies, septal deviation, or environmental irritants. Turbinate reduction shrinks the tissue volume and can meaningfully improve airflow. What it does not do is correct structural collapse, a separate and often coexisting problem that requires a different technical approach entirely.
Internal and external nasal valve collapse
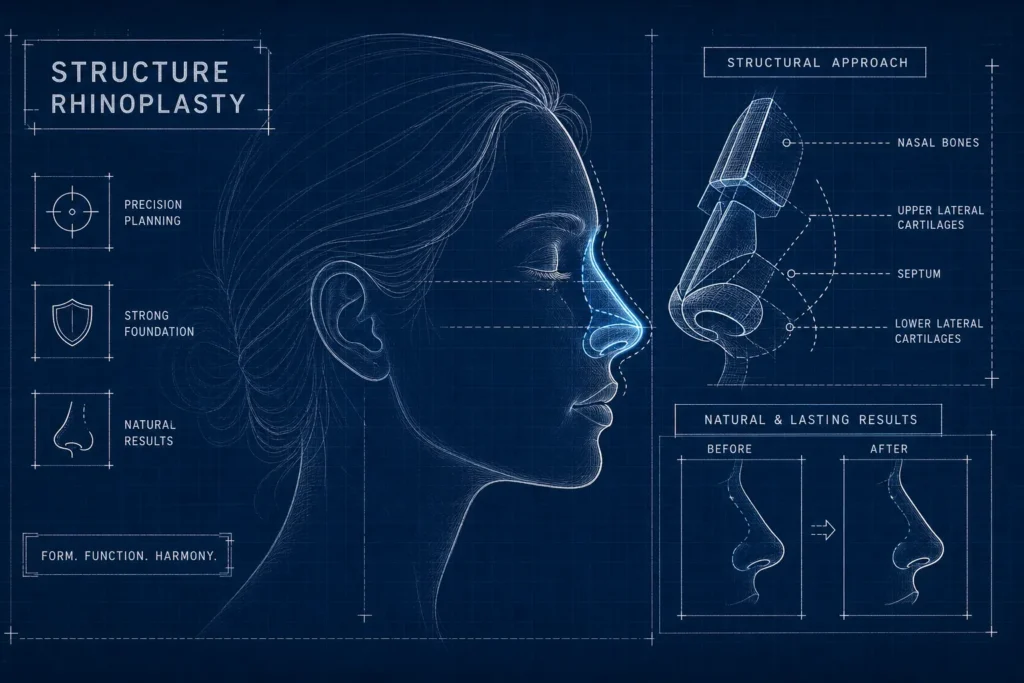
The internal nasal valve is the anatomically narrowest point in the entire airway, located just inside the nostrils where the upper lateral cartilages meet the septum. Most patients have never heard of it, but when it narrows or collapses, the restriction to airflow is severe. External valve collapse is a related but distinct problem: the alar walls of the nose are structurally weak and collapse inward during deep inhalation. You can sometimes reproduce external collapse yourself by pressing a finger gently against your cheek while inhaling. If that opens your breathing noticeably, you likely have an external valve component. Neither of these problems responds to septoplasty or turbinate reduction. They require structural reconstruction. For a clear clinical overview of nasal valve collapse and its functional impact, reliable patient-facing resources can be helpful.
How functional rhinoplasty differs from septoplasty and cosmetic surgery
These procedures are frequently confused with one another. That confusion leads patients to pursue the wrong surgery first, experience incomplete results, and then undergo a second procedure that could have been avoided entirely, often because a patient chose isolated septoplasty when nasal valve collapse was the real driver of obstruction. If you want a concise professional explanation of the distinctions, see the discussion on the difference between cosmetic and functional rhinoplasty.
Septoplasty vs. functional rhinoplasty: different targets, different outcomes
Septoplasty is performed entirely inside the nose. There are no external incisions, no change to the nose’s appearance, and the sole target is the deviated septal wall. It’s the right surgery when a deviated septum is the primary driver of obstruction and the nasal valves are structurally sound. Functional nasal surgery, by contrast, addresses the support framework of the nose itself, which means it can produce subtle external changes even when no cosmetic intent exists. For patients whose obstruction originates in valve collapse rather than septal deviation, septoplasty will not provide durable relief.
Where cosmetic rhinoplasty fits in (and where it doesn’t)
Cosmetic rhinoplasty prioritizes shape and symmetry. Any breathing improvement that results is incidental, not guaranteed, and not the surgical target. Septorhinoplasty is the formal term for a combined procedure that corrects the septum and reconstructs the external framework simultaneously. It is the most comprehensive option for patients dealing with both functional obstruction and aesthetic concerns, yielding stronger improvements in validated outcome scores than septoplasty alone when valve insufficiency is also present.
The case for fixing breathing and appearance in one surgery
Patients who want both improved breathing and a refined appearance often face the question of sequencing: fix the breathing first, then do cosmetic surgery later? The logic seems reasonable, but the surgical reality points in a different direction.
Why two separate procedures is rarely the better path
Two surgeries mean two separate anesthesia events, two full recovery periods, and two sets of surgical fees. Beyond the cost and inconvenience, there’s a clinical problem: scar tissue from the first surgery can complicate the second. If the first procedure altered internal cartilage architecture, the surgeon performing the second has less predictable anatomy to work with, particularly in the tip and valve areas. Combining both goals into a single operation eliminates that risk entirely and typically results in a shorter total recovery compared to the cumulative time of two staged procedures. If you’d like to read a practical patient-focused explanation of how surgeons can fix a deviated septum and reshape your nose at once, that resource outlines the combined approach used at Op. Dr. Ergün Kürün’s clinic.
How ENT-trained surgeons approach this differently
General plastic surgeons are trained to treat the nose as a cosmetic structure. ENT surgeons treat it as an airway that also has aesthetic dimensions. At Op. Dr. Ergün Kürün’s clinic in Adana, every surgical plan begins with an endoscopic nasal function evaluation, included as part of the free initial consultation, so that breathing correction and aesthetic refinement are integrated from the first visit rather than addressed separately. This dual-trained approach means patients with functional and cosmetic goals can resolve both in a single operation, without the complications that staged surgeries can introduce. For international patients evaluating options, that single-operation model is one of the most clinically and practically compelling advantages the clinic offers.
What happens during the surgery: techniques surgeons use
Understanding the basic mechanics of functional rhinoplasty reduces anxiety considerably. You don’t need to know every surgical detail, but knowing what the main techniques accomplish gives you a framework for the consultation conversations that matter most.
Open vs. closed approach and what each means for you
A closed approach uses incisions placed entirely inside the nostrils, leaving no visible scar. An open approach adds a small incision across the columella, the narrow strip of tissue between the nostrils, which allows the surgeon to lift the skin and see the entire nasal framework directly. For nasal valve reconstruction, the open approach is standard because accurate graft placement requires that level of visualization. Combined procedures run approximately 2 to 2.5 hours under general anesthesia. Revision cases, where existing scar tissue must be navigated, typically take longer.
Spreader grafts, alar batten grafts, and cartilage sourcing
Spreader grafts are thin strips of cartilage placed between the upper lateral cartilages and the dorsal septum. Their purpose is to widen a collapsed internal valve and hold it open structurally. Alar batten grafts serve a different function: they reinforce the sidewall of the nose to prevent external valve collapse during inhalation. Cartilage sourced from the nasal septum is the first choice for both graft types; when greater volume or structural strength is needed, cartilage from the ear or rib is used instead. Internal splints are placed at the close of surgery and typically removed between day one and day seven, depending on the extent of septal work performed.
Recovery timeline and realistic outcomes
Most patients describe recovery as more manageable than anticipated, particularly when they have a clear sense of what each phase involves. The timeline below reflects what the majority of primary functional rhinoplasty cases look like in practice.
What the first two weeks actually look like
Swelling, bruising, and nasal congestion peak within the first 72 hours and begin declining noticeably by the end of week one. Splints and external tape are typically removed around day seven, and most patients return to social life within that window. Strenuous exercise and contact sports are restricted for four to six weeks to protect the reconstructed structures while they integrate and stabilize. Driving is generally cleared once prescription pain medication is no longer needed. For practical guidance on travel timing and safety, including advice about flying home after rhinoplasty, review the clinic recommendations before you book return travel.
How long before you breathe noticeably better
Functional improvement is measurable at six weeks, when healing is approximately 40% complete, and becomes significant by six months, when healing reaches roughly 70%. Published outcome data shows that 90 to 95% of primary functional rhinoplasty patients achieve meaningful breathing improvement. To put the quality-of-life gain in perspective: studies using validated obstruction scoring report average NOSE score improvements of approximately 40 points following spreader graft placement, far exceeding the 15-point threshold considered clinically significant, and 96.2% of patients report good to moderate functional satisfaction postoperatively. Full healing, including complete resolution of internal swelling, takes up to 12 months, but breathing outcomes improve well before cosmetic refinements fully settle.
How to choose the right surgeon for this procedure
The surgeon’s training background matters more for functional rhinoplasty than for most cosmetic surgeries. The technical demands of nasal airway reconstruction require specialty-specific knowledge that not every rhinoplasty provider has.
The credentials that actually matter for functional work
Board certification in otolaryngology (ENT) or facial plastic surgery is the baseline. Demonstrated experience with nasal valve repair specifically, not just septal correction, is a further qualifier. A surgeon who performs an endoscopic nasal function evaluation before surgery, rather than relying solely on a visual consultation, is signaling that airway anatomy is central to how they plan cases. That evaluation is where structural problems like valve collapse are identified, and without it, surgical plans can miss the actual source of obstruction.
Questions to ask before you commit
Three questions will quickly reveal whether a surgeon has genuine functional expertise.
“Do you address the nasal valves, or only the septum?” A surgeon who addresses only the septum is offering septoplasty, not functional nasal surgery.
“Will you plan for both breathing and appearance goals in a single procedure?” This reveals whether the provider integrates ENT and aesthetic knowledge or treats them as separate concerns.
“Can I see before-and-after cases that include documented functional outcomes, not just appearance photos?” Surgeons who are confident in breathing results will have the outcome data to show for it.
Patients seeking ethnic-specific expertise or evaluating surgeons for particular facial features may also appreciate targeted guidance on selecting a specialist; if you are researching providers for Middle Eastern anatomy, see this discussion on finding the right specialist for Middle Eastern rhinoplasty.
Taking your next step
Nasal airway surgery corrects the structural causes of chronic obstruction, whether that’s a deviated septum, enlarged turbinates, or a collapsing valve. It is distinct from basic septoplasty and from cosmetic rhinoplasty, though it can be combined with either when the clinical picture calls for it. The strongest outcomes come from surgeons who assess airway anatomy before planning any incision and who bring the ENT foundation that this type of reconstruction requires.
If you’re exploring functional rhinoplasty, whether domestically or abroad, the consultation itself is the most important first step. At Op. Dr. Ergün Kürün’s specialized clinic in Adana, the initial consultation includes an endoscopic nasal function evaluation at no charge. That single appointment can clarify exactly which anatomical problems are driving your obstruction and whether a combined functional and aesthetic approach makes sense for your goals. It’s the most direct path from chronic frustration to an informed surgical plan.