A middle eastern nose job demands more than removing a hump or narrowing a bridge. It requires anatomy-specific planning, technique selection built around thick skin and weak cartilage, and a surgeon whose entire approach is calibrated to this structural profile from the first consultation forward. Most rhinoplasty failures in Middle Eastern patients trace back to one root cause: a surgeon applying a generic technique to anatomy that simply doesn’t respond the same way. Whether your heritage is Persian, Arab, Turkish, or North African, your nose carries a distinct structural profile that changes what’s surgically possible, which techniques hold long-term, and what a truly natural result actually looks like. A surgeon can remove a dorsal hump with reasonable technical skill and still leave you with a shapeless, over-reduced nose that looks nothing like it belongs on your face.
This guide covers what makes Middle Eastern rhinoplasty categorically different, which surgical approaches are built for this anatomy, how healing actually unfolds, what you should budget, and how to verify that a surgeon has genuine experience before you commit. Surgeons who approach this work seriously begin with concrete priorities, framework reconstruction, grafting sequencing, and radix planning, rather than applying the same reduction protocol they use for every other patient.
Why Middle Eastern noses require a specialized surgical approach
The anatomy is specific, and understanding it matters before you walk into any consultation. Middle Eastern noses consistently present with five core structural traits: thick sebaceous skin, weak lower lateral cartilages, a prominent dorsal hump, a wide or bulbous nasal tip, and a low nasal radix. These features don’t exist in isolation. The heavy skin drapes over weak cartilage, which is precisely why the tip looks bulbous and undefined even before surgery enters the picture.
The low radix creates an additional planning complication that many surgeons miss entirely. When the bridge between the eyes sits low, it makes the dorsal hump appear significantly larger than it actually measures on the skeleton. A surgeon who reduces the hump without accounting for this optical relationship can create a profile that looks disproportionate even after technically successful bone work. The solution often involves radix augmentation alongside hump reduction rather than straightforward shaving alone.
Thick skin changes the entire equation for surgical outcomes. A thin-skinned patient reveals fine cartilage detail within a few months; a thick-skinned patient may see very little visible definition for 12 months post-surgery. This is biology, not surgical failure. It means the surgeon must build a stronger, more prominent internal framework than they would use for thinner skin. In more pronounced cases, soft-tissue de-fattening (sub-dermal defatting) becomes part of the plan. Patients who don’t understand this often panic at month three and book revision consultations they don’t actually need.
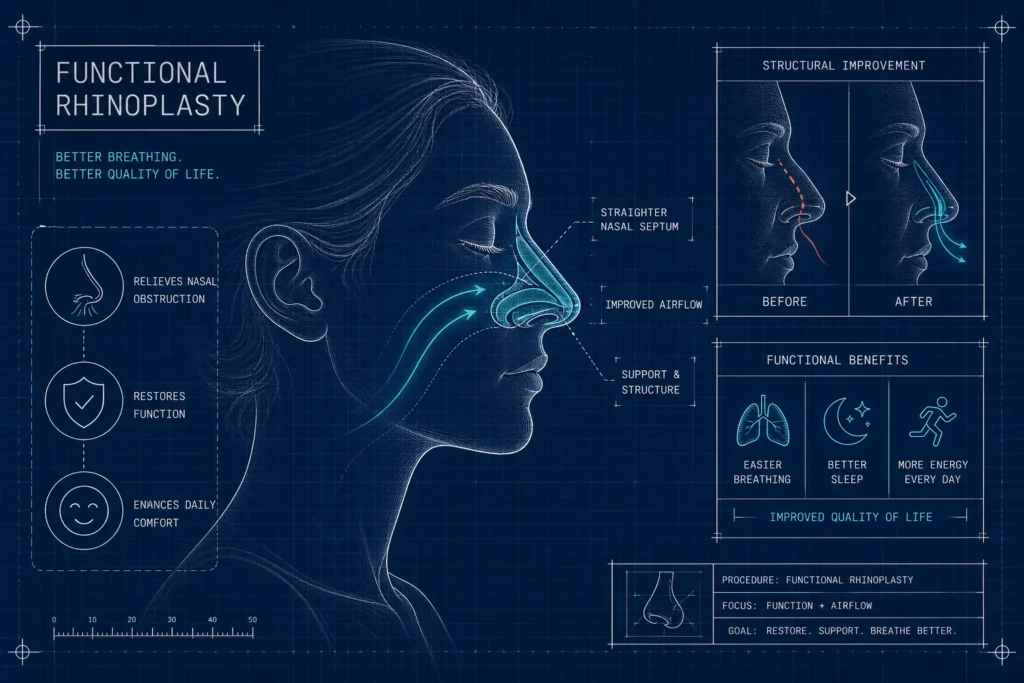
Three areas consistently underestimated in surgical planning are the alar base, the caudal septum, and the upper lateral cartilage width. These aren’t secondary concerns you address if time permits, they directly affect both the aesthetic result and nasal airway function. Many Middle Eastern patients also carry some degree of functional pathology, such as septal deviation or turbinate hypertrophy, making combined septorhinoplasty the most complete and efficient approach for this population.
Surgical techniques for a Middle Eastern nose job that preserves ethnic identity
Middle Eastern rhinoplasty requires methods that respect both form and function. Open rhinoplasty is the standard access route for this anatomy because direct visibility of the entire cartilaginous framework is essential when a surgeon needs to place grafts precisely and execute complex tip maneuvers. Closed rhinoplasty limits access to a degree that makes the structural work Middle Eastern noses require significantly harder to execute reliably. The external scar placed at the columella is often inconspicuous once healed, and the precision it enables is a worthwhile trade-off for most patients.
Structural grafting
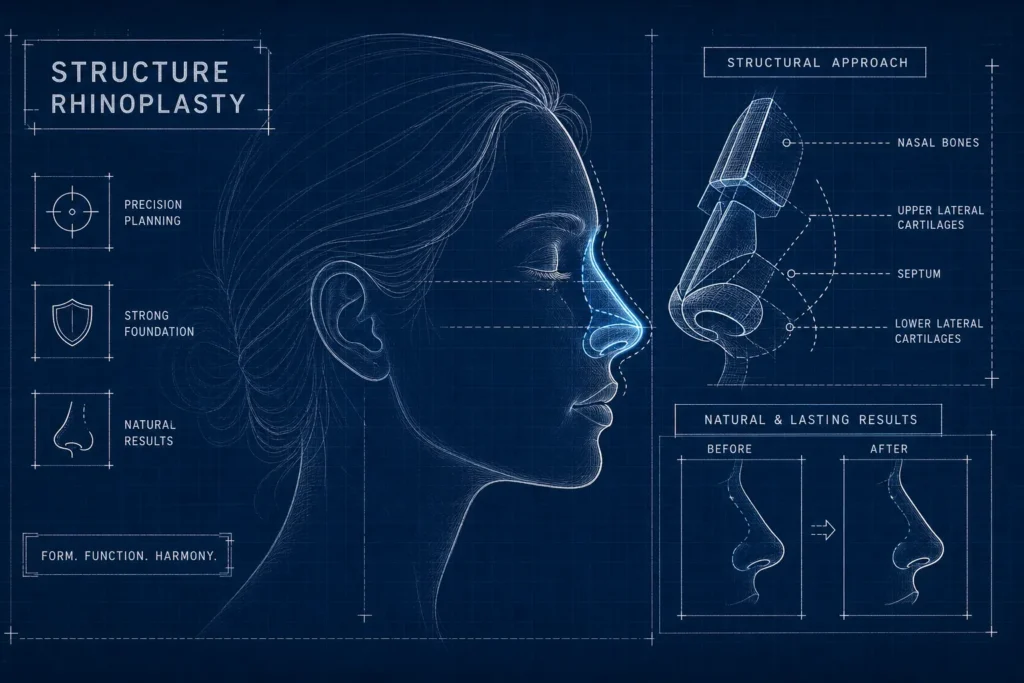
Structural grafting is where the real surgical work happens. The columellar strut prevents tip drooping, especially when smiling, which is one of the most common complaints after poorly planned ethnic rhinoplasty. Tip grafts create definition capable of penetrating through thick skin where sutures alone won’t hold. Spreader grafts reduce the risk of inverted-V deformity after hump reduction when used appropriately as part of the plan.
For tip refinement, lateral crural steal increases projection and adds structural strength to weak lower lateral cartilages; tongue-in-groove technique secures the medial crura to the caudal septum for lasting stability. Tip suturing alone, interdomal or intercrural, is frequently insufficient for this anatomy. Grafts are frequently essential in Middle Eastern rhinoplasty to achieve lasting definition and support, especially when cartilages are weak.
Cartilage sources
When it comes to cartilage sources, the clinical hierarchy places septal cartilage first, auricular (ear) second, and costal (rib) third. Septal cartilage is the gold standard for spreader grafts, septal extension grafts, and columellar struts. When the septum doesn’t provide enough material, which happens with regularity in this anatomy, conchal cartilage from the ear steps in, particularly for lateral crus replacement, because its natural curve closely matches the shape of the alar cartilage. The role of cartilage grafting in ethnic rhinoplasty explains why surgeons layer graft choices based on structural needs. Rib cartilage is reserved for major reconstruction cases, revisions, or situations where both prior sources have been depleted.
Preservation rhinoplasty
Preservation rhinoplasty, which keeps the dorsal ligamentous complex intact, is gaining momentum in the surgical world and has real merit for the right patient. For many Middle Eastern patients, though, it isn’t the primary approach. When a prominent dorsal hump needs reduction and the internal framework needs reinforcement, preservation techniques apply selectively rather than universally. Any clinic presenting preservation rhinoplasty as the automatic solution for this anatomy, without evaluating the case individually, is applying a protocol that doesn’t fit the problem.
Recovery after a Middle Eastern nose job
The first week involves a nasal splint, significant swelling, bruising, and congestion, all of which are expected. When the splint comes off at day seven, bruising begins to fade and most patients can return to non-strenuous work. By weeks two and three, visible bruising clears and most people feel comfortable re-entering public life.
Breathing improvement becomes noticeable in months one through three, while tip swelling remains pronounced throughout this phase. Some clinics that operate with a structured post-operative protocol give patients a clear roadmap for navigating these stages rather than leaving them to interpret every change with anxiety. The final result for thick-skinned patients takes 12 to 18 months to fully settle, and sometimes longer. This is not an extended timeline to apologize for; it’s the expected biology of thick skin contracting slowly around a new internal framework. Tip definition is the last feature to emerge. Clinical series focusing on Middle Eastern rhinoplasty indicate that revisions driven by aesthetic dissatisfaction most commonly involve the nasal tip, and many of those consultations happen before the final result has actually appeared. Understanding this timeline upfront is what separates a patient who waits confidently from one who pursues an unnecessary second surgery.
What a middle eastern nose job costs and why many patients look beyond the US
A middle eastern nose job performed by a specialist in the United States typically runs between $10,000 and $25,000. The national average for ethnic rhinoplasty sits around $8,200, but surgeons with verified experience in this anatomy and practices in cities like New York, Los Angeles, or Washington D.C. regularly start at $15,000 to $20,000 before any complexity adjustments. The cost drivers are layered: surgical complexity often bundles grafting, septoplasty, and alarplasty together; specialist premiums apply for surgeons with a focused ethnic rhinoplasty practice; anesthesia is billed separately at $800 to $1,500; and facility fees add another $1,000 to $2,000. Insurance may cover the functional components if medically documented, but the aesthetic portion is always out-of-pocket.
Turkish rhinoplasty costs 60 to 70 percent less than equivalent US procedures, with ethnic rhinoplasty at specialist clinics in Istanbul and Adana ranging from $4,000 to $6,500 in 2026, compared to $12,000 to $16,000 and above in major American cities. That gap remains significant even after accounting for flights and accommodation. Op. Dr. Ergün Kürün’s practice in Adana, Rinoplasti & Burun Estetiği Kliniği, is built specifically around this type of case. With an ENT specialist background and a focus on ethnic rhinoplasty, Dr. Kürün works directly with each patient through consultation, surgery, and follow-up, integrating digital pre-surgical planning and golden ratio facial analysis adapted to ethnic proportions. For Middle Eastern-American patients, that cultural and clinical familiarity shapes the entire interaction from the first teleconsultation onward. If you’re weighing options, read more on whether rhinoplasty in Turkey is worth it for American patients.
How to find a surgeon who genuinely specializes in ethnic rhinoplasty
The consultation questions that separate specialists from generalists are direct and non-negotiable. Ask how many Middle Eastern rhinoplasty cases the surgeon performs each year. Request before-and-after photos specifically of Persian, Arab, or Turkish noses. Ask exactly how they address a bulbous tip in a patient with thick skin and weak lower lateral cartilages. A surgeon who deflects these questions, offers generalizations, or can’t show you a relevant portfolio isn’t your specialist, regardless of how impressive their general credentials appear. Also ask about revision policy: what happens if you’re not satisfied, and at what cost to you. For a practical checklist on finding the right specialist, look for surgeons who can answer these items clearly and with case-specific examples.
Board certification by the American Board of Plastic Surgery or the American Board of Facial Plastic and Reconstructive Surgery establishes baseline technical competency. Certification alone, however, doesn’t prove ethnic rhinoplasty expertise. Portfolio review is the real filter. You’re looking for a specific quality in the results: noses that look naturally refined, not surgically generic, and not ethnically erased. The before-and-after photos should show patients who look like sharper, better versions of themselves, not like they’ve been reshaped toward a different ethnic template. In clinical studies focusing on ethnicity-conscious surgical approaches, tailored techniques have been associated with meaningfully lower revision rates compared to non-tailored methods. That difference reflects what specialized planning actually accomplishes.
At Dr. Kürün’s clinic, surgical planning begins with digital pre-surgical visualization and facial analysis before a single incision is discussed. His ENT background means breathing function and aesthetics are addressed simultaneously in every case. His working command of preservation, structural, and ultrasonic (Piezo) rhinoplasty techniques gives each Middle Eastern patient a plan built for their specific anatomy rather than a fixed protocol applied across the board. For patients traveling from the United States, the clinic provides teleconsultation and English-language support from the first inquiry through post-operative follow-up.
Making the right decision starts with the right questions
A middle eastern nose job done well is a precise, anatomy-specific procedure. Thick skin, weak cartilage, and the structural demands of building a durable internal framework all require a surgeon who understands this anatomy in depth, not simply a surgeon who has performed rhinoplasty in general for many years. Realistic expectations, a verifiable ethnic rhinoplasty portfolio, and honest pre-operative planning are what separate lasting results from early revision appointments.
Whether you choose a US-based specialist or travel for care, the evaluation criteria don’t change. The surgeon’s experience with Middle Eastern anatomy is non-negotiable, and it’s the right first question to ask in any consultation. When you’re ready to take that step, a structured consultation with a surgeon who has built their practice around exactly this type of case is where clarity begins. To explore whether Dr. Kürün’s approach is the right fit for your anatomy and goals, reach out to the clinic directly to arrange a teleconsultation.